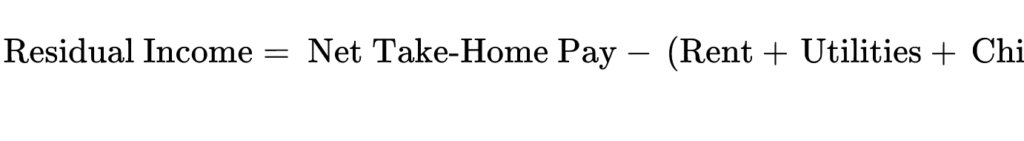A Meal Divided Into Tomorrow
In the quiet, late-afternoon light of a modest apartment, the daily ritual of survival begins with a careful division of resources. An elderly individual stands at the kitchen counter, meticulously portioning a single can of low-sodium soup into two separate bowls. One bowl is heated for the evening meal; the other is sealed with plastic wrap and placed in a largely bare refrigerator alongside a few slices of bread and several expired condiments. To the casual observer, nothing in the room announces an immediate crisis. The apartment is orderly, the utility bills are stacked neatly on a side table, and the resident, if asked by a visiting nurse or relative, will undoubtedly insist that everything is fine. Yet, the refrigerator contains the undeniable evidence of a quiet, disciplined deprivation.
This is the architecture of modern senior hunger. It does not look like overt starvation in the public square; it looks like containers stretched across multiple days, coffee diluted with excess water, and meals skipped entirely under the guise of a lost appetite1. In 2022, empirical data indicated that 6.9 million seniors in the United States—roughly one in eleven adults aged 60 and older—experienced food insecurity2. For older adults aged 50 to 59, the numbers are even more severe, with one in eight individuals (11.9%) experiencing food insecurity2. This crisis represents a persistent elevation from pre-pandemic baselines, exacerbated by aggressive inflation in the food sector3.
With the senior population projected to grow to 104 million by 2050, demographic modeling suggests that without radical systemic intervention, over 7 million older adults will soon be trapped in a permanent state of nutritional deficit4. Despite its staggering prevalence, this form of hunger remains largely invisible, locked behind closed apartment doors and shrouded by a generation’s determination not to become a burden. The crisis is defined not merely by an absence of calories, but by a daily, agonizing negotiation between nourishment, medication, spatial isolation, and human dignity.
The Invisible Architecture of Pride, Stigma, and Isolation
To comprehend why senior food insecurity remains so thoroughly concealed, one must examine the psychological and sociocultural forces that differentiate it from the hunger experienced by younger demographics. Child hunger is frequently detected by external observers within the public sphere—teachers noticing a lack of focus, pediatricians tracking developmental milestones, or school administrators observing chronic absenteeism5. Conversely, an older adult living alone may go days or weeks without meaningful interaction with mandatory reporters or social service networks. By 2021, approximately 27% of older adults lived alone, including 43% of women aged 75 and over, a demographic reality that significantly compounds the risk of invisible starvation6.
The most formidable barrier to visibility, however, is deeply internalized. Many older adults were socialized within a cultural paradigm that prized absolute self-reliance, thrift, and extreme privacy1. Within this generational mindset, asking for charitable food assistance is often perceived not as utilizing a basic safety net, but as a public admission of personal failure. Gerontological research into the lived experience of elderly food insecurity reveals that utilizing food pantries or applying for public benefits routinely triggers profound feelings of shame, social stigma, and a perceived loss of dignity1. Qualitative interviews with seniors demonstrate a reluctance to utilize private food assistance programs, with individuals frequently citing the stigma of the pantry line and the “hurt pride” associated with receiving handouts1.
Furthermore, a pervasive myth exists among many seniors that safety net resources are inherently scarce. Older adults frequently refuse aid under the erroneous belief that they are taking food away from “someone who needs it more,” such as an impoverished family or a starving child7. This stoic independence acts as an impenetrable, invisible wall. When families or social workers do interact with these individuals, the hunger is hidden by habitual deflection. The older adult will claim they have already eaten, or that their digestion simply cannot handle large meals anymore7. The crisis remains concealed by pride, perpetuated by systemic isolation, and tolerated by a society that often overlooks its aging population until a catastrophic medical event forces the physiological damage of malnutrition into the light.
Demographic Disparities in Senior Deprivation
The burden of senior hunger is not distributed equally across the aging population. It fractures along deep, historical fault lines of race, ethnicity, disability, and family structure. The data reveals that the probability of aging into starvation is heavily predicated on lifelong exposure to systemic inequities.
| Demographic Subgroup (Seniors 60+) | Food Insecurity Prevalence (2021/2022 Data) | Systemic Implication |
| Overall Senior Population | 8.7% (1 in 11) | A baseline representing nearly 6.9 million individuals lacking consistent access to adequate nutrition2. |
| Black Seniors | 3.8x higher than White seniors | Reflects lifelong wage disparities, redlining, and exclusion from generational wealth accumulation4. |
| Latino / Hispanic Seniors | 3.0x higher than White seniors | Correlates with higher rates of employment in sectors lacking pensions and higher concentrations in food apartheid zones4. |
| Seniors with Disabilities | 13.4% | Over twice as high as seniors without disabilities (5.0%), driven by extraordinary medical costs and physical immobility4. |
| Multigenerational Households | 15.0% (Living with grandchildren) | Financial resources are heavily diluted; older adults routinely sacrifice their own caloric intake to feed dependent children4. |
| Seniors Living Alone | 11.4% | Lack of pooled household income and severe vulnerability to social isolation6. |
The intersectionality of these statistics creates devastating pockets of hyper-vulnerability. For example, a disabled Black woman living alone faces a compounded risk that virtually guarantees nutritional deficit4. Similarly, the phenomenon of the “grandparent caregiver” introduces a profound element of sacrificial hunger. When a household budget collapses, an older adult raising grandchildren will instinctively default to a protective posture, serving the youth first and consuming only the remnants, thereby transforming their own starvation into an active expression of familial obligation4.
The Fixed-Income Funnel and the Arithmetic of Poverty
The mechanics of senior food insecurity are inextricably linked to the rigid mathematics of the “fixed-income funnel.” For millions of older adults, financial survival is dictated entirely by a monthly Social Security or Supplemental Security Income (SSI) deposit. While this income remains effectively static—adjusted only by an annual Cost-of-Living Adjustment (COLA) that frequently lags behind real-time inflation—the expenses it must cover are subjected to relentless market pressures9.
By tracing the trajectory of a monthly benefit check, the extreme vulnerability of the grocery budget becomes glaringly apparent. The SSI program, administered by the Social Security Administration (SSA), provides a baseline income for the aged, blind, and disabled who possess little to no other resources10. For 2026, the maximum federal SSI payment for an individual is set at $994 per month9. Certain states, recognizing the inadequacy of the federal baseline, provide a State Supplementary Payment (SSP). In California, the maximum SSP for an individual in 2026 is projected at $239.94, bringing the absolute maximum combined monthly grant to $1,233.9412.
| Budget Line Item | Estimated Monthly Cost / Deduction | Remaining Household Balance | Systemic Rationale |
| Maximum SSI/SSP Grant (CA 2026) | $1,233.94 | $1,233.94 | Leaves the individual at approximately 93% of the Federal Poverty Level; functionally institutionalizes deep poverty12. |
| Rent (Studio/1-Bedroom) | -$850.00 (Highly Subsidized) | $383.94 | Rent routinely consumes more than 50% of the SSI grant in all 58 California counties13. |
| Utilities (Electric, Water, Heating) | -$120.00 | $263.94 | Required to maintain habitability and prevent fatal exposure to extreme temperatures. |
| Medicare Premiums & Copays | -$85.00 | $178.94 | Essential for managing chronic diseases and securing life-saving pharmaceuticals. |
| Transportation & Telecommunications | -$60.00 | $118.94 | Necessary for medical transit and preventing total social isolation. |
| Residual Income for Food | -$118.94 | $0.00 | Leaves less than $4.00 per day for all dietary, household, and hygiene needs. |
Rent occupies the unyielding top tier of this economic funnel. For older adults who do not own their homes, the threat of eviction is a constant terror. Data indicates that seniors who rent experience food insecurity at over three times the rate of those who own their homes6. Furthermore, individuals experiencing homelessness aged 50 and over face a food insecurity rate five times higher than the general older population6.
After housing, utilities, medical premiums, and basic telecommunications are extracted, the remaining capital—the residual income—is frequently negligible13. Because a lease agreement cannot be negotiated and utility companies will ruthlessly terminate service for non-payment, food becomes the ultimate shock absorber in the budget. It is the only elastic line item. When a utility bill spikes during a winter freeze, the senior does not default on their rent; they simply stop buying fresh produce and lean proteins, substituting nutrient-dense foods for cheap, highly processed calories, or skipping meals entirely6.
The Medicine-or-Meals Calculation and Clinical Consequences
When residual income drops near zero, older adults are forced into a harrowing daily triage: the choice between life-sustaining medication and basic sustenance. This “medicine-or-meals” calculation is one of the most lethal tradeoffs manufactured by systemic poverty.
Many chronic conditions prevalent in aging populations—such as hypertension, Type 2 diabetes, and Chronic Obstructive Pulmonary Disease (COPD)—require strict adherence to complex pharmacological regimens14. However, individuals facing food insecurity frequently ration their prescriptions, delay vital refills, or split pills in half to ensure they have enough capital left to purchase groceries7. Conversely, they may fully fund their pharmacy copayments but subsequently starve themselves to absorb the financial blow.
This calculation is inherently contradictory and biologically destructive. Medications designed to manage chronic illness often require administration alongside adequate, nutritious food to prevent severe gastrointestinal damage or dangerous fluctuations in blood chemistry. The clinical consequences of this forced choice are vast. Research demonstrates that individuals living in food-insecure households use more prescription medications and experience significantly higher rates of hospitalizations, resulting in an estimated $77.5 billion in excess healthcare spending annually in the United States16.
In populations with uncontrolled Type 2 diabetes, patients facing food insecurity exhibit significantly higher hemoglobin A1c (HbA1c) levels15. When an older adult takes insulin but cannot afford the food required to stabilize their glycemic index, the medical intervention itself becomes a catalyst for hypoglycemic shock. Similarly, individuals with COPD who experience food insecurity and utility shutoff threats face exacerbated respiratory decline due to the stress and physical toll of economic precarity14. The paradox is absolute: the financial resources expended by the state to preserve senior health actively deplete the nutritional resources required for the senior to survive.
The Physicality of Access: Aging, Mobility, and the Built Environment
The definition of “food access” is frequently reduced by urban planners to a matter of geographic proximity—the distance in miles between a residence and the nearest supermarket. However, for an aging population, access is fundamentally a question of physical capability. The built environment of the modern grocery store is entirely unsuited to the biological realities of aging.
As individuals age, they frequently encounter compounding physical limitations that severely impair Activities of Daily Living (ADLs). Osteoarthritis degrades joint mobility, macular degeneration impairs vision, and sarcopenia reduces muscular strength6. A supermarket located a mere half-mile away may be geographically close, but if reaching it requires navigating cracked sidewalks with a walker, the store is effectively unreachable.
Once inside the retail environment, the physical demands escalate. Reaching for a discounted item on a bottom shelf requires painful crouching, while reading the microscopic font of expiration dates requires visual acuity that many older adults no longer possess. Furthermore, the economics of bulk purchasing are completely negated by physical frailty. A ten-pound bag of rice or a gallon of milk may represent the most cost-effective caloric purchase, but if an eighty-year-old woman cannot physically lift the item into her cart, carry it onto a bus, and transport it up two flights of stairs to her apartment, the economic advantage is irrelevant1. For the elderly, accessibility is measured not just in transit miles, but in the weight of the bags, the height of the shelves, and the physical endurance required to complete the transaction.
Transportation: The Missing Link and Rural Isolation
The loss of driving privileges is a devastating milestone in the aging process, instantly severing an older adult’s primary mechanism of independence. When the car keys are surrendered, the logistics of food procurement collapse, revealing transportation as the critical, missing link between food assistance and actual meals7.
Public transportation networks, particularly outside of dense urban cores, are frequently inadequate for the needs of the elderly. Bus routes may require long waits in extreme weather, and the vehicles themselves pose severe fall risks during boarding and disembarking. Paratransit services, while designed for individuals with disabilities, demand rigid advance scheduling, offer highly unpredictable pickup windows, and routinely impose strict limits on the number of grocery bags a passenger is permitted to transport7.
When formal transit systems fail, seniors are forced to rely on expensive taxi services or rideshare applications. A fifteen-dollar round-trip rideshare fare instantly vaporizes the savings achieved by traveling to a discount supermarket. Alternatively, seniors must depend on the sporadic goodwill of relatives, neighbors, or volunteers7. This reliance fundamentally alters the nature of the grocery trip, transforming a basic act of self-care into a continuous imposition on others. The senior must rush their shopping to avoid inconveniencing their volunteer driver, stripping them of their autonomy and reinforcing the emotional weight of their dependency. In rural areas, this transportation deficit is catastrophic. A rural senior may live miles from the nearest full-service grocery store, rendering them entirely dependent on inconsistent supply lines and vulnerable to severe malnutrition7.
The SNAP and CalFresh Gap: The Papercut Prison of Enrollment
Given the severity of the fixed-income funnel, the Supplemental Nutrition Assistance Program (SNAP)—known as CalFresh in California—should serve as the ultimate bulwark against senior hunger. The program is exceptionally effective; SNAP substantially reduces the prevalence of food insecurity and mitigates negative health outcomes18. However, the program is plagued by a catastrophic participation gap among older adults.
While overall SNAP participation rates for the general population are robust, historic data indicates that only 42% of eligible elderly individuals nationwide actually enroll in the program, leaving millions of vulnerable seniors without critical aid19. In California, the participation rate among eligible seniors has historically been one of the lowest in the country. At its nadir in 2012, only 19% of eligible people over 60 in California were enrolled in SNAP, a massive systemic failure in a state with the fourth-highest number of eligible seniors19. Currently, roughly 1.5 million California seniors qualify for CalFresh yet remain unenrolled20.
The barriers to enrollment constitute a “papercut prison” of administrative friction. Many seniors operate under the misconception that claiming benefits will somehow negatively impact their Social Security payments, or they are deterred by the complex, invasive paperwork required7. Navigating online portals requires digital literacy and broadband access that many low-income seniors lack7.
Conversely, states that have actively dismantled these barriers provide a blueprint for success. Massachusetts dramatically improved its senior SNAP participation rate from 16% in 2002 to 67% in 2015 by implementing systemic reforms: waiving interviews for elderly beneficiaries, establishing a standard medical expense deduction of $155, simplifying the application to two pages, creating a statewide call center, and extending the certification period to 12 months19.
In California, efforts to close this gap include the Elderly Simplified Application Project (ESAP), which targets households where all members are aged 60 or older and have no earned income, extending certification periods to 36 months and waiving interview requirements21. Furthermore, the reversal of the SSI “cash-out” policy in 2019 allowed SSI recipients in California to finally apply for CalFresh, prompting massive state-funded outreach efforts through Area Agencies on Aging (AAAs)20.
However, the looming threat of the federal “One Big Beautiful Bill Act” (H.R. 1) casts a dark shadow over this progress. Proposals to cut federal SNAP spending by $186 billion to $295 billion over a decade threaten to shift massive administrative costs onto state agencies and strip benefits from millions23. When state agencies are underfunded, bureaucratic friction worsens, vulnerable seniors are ejected from the program due to simple clerical errors, and the fragile safety net collapses entirely.
Meals on Wheels: The Infrastructure of Care and the Funding Chasm
For homebound seniors who cannot navigate the physical or logistical hurdles of the grocery store, the home-delivered meal represents the absolute final line of defense. Programs like Meals on Wheels deliver far more than a tray of heated food; they deliver a critical clinical intervention against the lethal consequences of malnutrition and profound social isolation7.
When a volunteer knocks on the door of a homebound elder, the brief interaction that follows is frequently the only human contact that individual will experience all day7. The delivery serves as an informal, vital wellness check. Volunteers are trained to notice if a senior appears confused, if previous meals remain uneaten, or if the residence poses a sudden safety hazard7. The evidence supporting this model is overwhelming: participation in home-delivered meal programs significantly improves dietary intake, reduces the risk of clinical malnutrition, and drastically lowers the rates of emergency room visits and hospital readmissions25.
Despite its proven efficacy, the infrastructure of home-delivered meals is currently buckling under immense financial strain. Funding provided by Title III-C of the Older Americans Act (OAA) has completely failed to keep pace with the exponential demographic growth of the aging population and the skyrocketing costs of food procurement and logistical operations28. The proposed federal FY2026 Budget allocates $1.059 billion for the OAA Nutrition Program, effectively flat-funding the initiative. However, advocacy groups emphasize that a minimum of $1.6046 billion is required merely to sustain current operations and address massive shortfalls25.
Consequently, the safety net is actively tearing. As of late 2024 and early 2025, one in three Meals on Wheels providers operates with an active waitlist25. Vulnerable seniors are languishing on these lists for an average of four months, with some waiting up to two years for a daily meal25. In Nevada, local providers like Catholic Charities are resorting to public raffles merely to raise the funds necessary to clear their growing waitlists, illustrating the desperate lengths required to fulfill a basic human need30. The tragic irony of this underfunding is profound: a Meals on Wheels program can sustain a senior in their home for an entire year with nutritious meals and safety checks at roughly the exact same cost as ten days in a long-term care facility or a single day in a hospital25. By starving the preventative infrastructure, society guarantees exorbitant downstream medical costs.
Congregate Meals and Senior Centers: Combating Isolation
While home delivery sustains the severely isolated, congregate meal programs at senior centers offer a powerful antidote to both hunger and loneliness for the ambulatory elderly. Funded similarly under Title III-C of the OAA, congregate settings mandate the simple, revolutionary act of breaking bread in a shared, communal space28.
A lunch served at a local senior center functions as an anchor point for the day. It provides a structured routine and actively rebuilds the social capital that naturally dissipates as peers pass away and mobility declines. Furthermore, the congregate site serves as a vital gateway to secondary interventions, offering blood pressure screenings, social worker consultations, and assistance with complex Medicare paperwork7. The environment fosters peer-to-peer support, where seniors share critical, localized information regarding affordable housing, effective medical providers, and navigating the complexities of public transit.
However, access to these congregate sites is not universal. Seniors dealing with early-stage cognitive decline, physical disabilities that require specialized feeding assistance, or deep-seated social anxiety may find these bustling environments overwhelming. Furthermore, cultural and linguistic barriers can profoundly alienate immigrant seniors who feel out of place in centers that do not serve culturally familiar foods or offer programming in their native languages7. Ensuring that congregate sites are radically inclusive, geographically distributed, and culturally competent remains a persistent challenge for municipal aging departments.
The Digital Aisle: Grocery Delivery as a Regressive Tax
In the wake of the pandemic, the rapid expansion of digital grocery delivery was heralded as a technological panacea for the homebound. On the surface, the ability to order fresh produce via a smartphone directly addresses the physical and transportation barriers that plague older adults. In practice, however, the digital aisle is rife with extractive mechanisms that transform convenience into a highly regressive tax on the poor.
The primary obstacle is the “fee stack.” Modern quick-commerce platforms unbundle the cost of food, attaching delivery fees, mandatory service charges, and expected driver gratuities to every transaction7. Crucially, federal regulations historically prohibited the use of SNAP or CalFresh Electronic Benefit Transfer (EBT) funds to pay for these logistical fees. A senior attempting to utilize their food benefits online is suddenly confronted with a “checkout cliff”—a demand for $15 to $20 in liquid cash merely to facilitate the delivery of their subsidized groceries. For a senior operating with zero residual income, this cash requirement renders the delivery application entirely useless7.
Beyond the financial extraction, the digital interfaces are frequently hostile to older users. Complex password resets, aggressive algorithmic substitutions that swap affordable staples for premium brands, and the lack of human customer service representatives create a frustrating, alienating experience. When a senior receives a delivery containing a substituted item they cannot physically chew or safely consume, the lack of an accessible recourse mechanism forces them to absorb the financial loss and go hungry7. Technology without intentional, empathetic design acts only as a modernized barrier.
The Dental, Dietary, and Biological Dimensions of Hunger
The calculus of senior food security must transcend the mere availability of calories and rigorously address the physiological ability to consume them. Aging introduces profound mechanical and biochemical limitations to eating. A generic food pantry box brimming with high-quality, dense nutrition—such as raw carrots, whole apples, and tough cuts of meat—is effectively useless to an older adult suffering from advanced periodontal disease, poorly fitting dentures, or dysphagia (difficulty swallowing)7.
Malnutrition in the elderly is a quiet, devastating epidemic, with prevalence rates in community-dwelling older adults ranging from 1% to nearly 20% in high-income nations26. The consequences of this malnutrition are catastrophic: it accelerates sarcopenia (muscle loss), degrades the immune system, compromises cardiovascular health, and exponentially increases the risk of severe falls, frailty, and subsequent hospitalizations26.
Standardized emergency food assistance rarely accounts for these physiological realities. Seniors managing congestive heart failure or renal disease require strictly controlled sodium intake, while those navigating advanced diabetes require complex carbohydrates and lean proteins. When charitable food networks distribute heavily processed, high-sodium canned goods, they inadvertently exacerbate the very chronic conditions that drive the senior’s medical costs higher7. Food availability is fundamentally distinct from usable, safe nourishment; an ethical food system must transition toward providing medically tailored meals that acknowledge the biological fragility of the aging body.
Three Portraits of the Invisible Crisis
To move beyond macroeconomic statistics, the crisis must be viewed through the distinct, lived experiences of the individuals trapped within it. Senior hunger is not a monolith; it mutates based on geography, housing status, and family structure7.
The Renter Living Alone
Evelyn, 78, resides in a modest apartment in Los Angeles County. She relies entirely on a survivor’s Social Security benefit. Evelyn is trapped in the epicenter of the housing crisis. Every year, her rent increases, silently devouring her stagnant income. By the twentieth of each month, her checking account holds less than twelve dollars. Evelyn does not complain to her landlord out of a paralyzing fear of retaliatory eviction. Instead, she enters a period of severe caloric restriction, drinking hot tea to suppress hunger pangs and eating only half-portions of oatmeal until the first of the month arrives. Her hunger is a direct, mathematical symptom of the real estate market7.
The Rural Elder
Harold, 82, lives in a decaying farmhouse in a remote, agricultural expanse. His nearest grocery store is fourteen miles away. Two years ago, failing eyesight forced Harold to surrender his driver’s license. He now resides in a profound transit and delivery desert. The gig-economy delivery platforms do not operate in his zip code, and public paratransit is non-existent. Harold’s sustenance relies entirely on a neighbor who drives into town once a week. Because he refuses to be an imposition, Harold asks for very little, subsisting primarily on canned soups and dry cereal. His geographic isolation has transformed his home into a solitary confinement cell7.
The Grandparent Caregiver
Maria, 69, represents a rapidly growing demographic: the multigenerational household anchor. She lives with her adult daughter and three young grandchildren. While there are immense cultural benefits to this structure, the economic strain is crushing. Statistical analysis reveals that food insecurity is 2.2 times higher for seniors residing with a grandchild compared to those living alone4. When the household budget collapses under the weight of inflation, Maria instinctively defaults to a sacrificial posture. She serves the children first, ensuring their plates are full of protein and fresh fruit, while claiming she has “already eaten” or simply isn’t hungry. Her starvation is an active, fiercely protective act of love7.
How Communities Notice—and Fail to Notice
Because senior hunger is actively camouflaged by pride and routine, detecting the crisis requires a heightened, empathetic vigilance from adult children, home-care aides, pharmacists, and community members7.
The indicators of food insecurity in an older adult are rarely explicit pleas for help. They manifest in subtle behavioral shifts and physical changes. Rapid, unexplained weight loss or increasingly loose-fitting clothing is a primary physiological alarm. A glance inside the refrigerator may reveal an unnatural emptiness, a hoarding of fast-food condiment packets, or the presence of heavily expired dairy products that the senior refuses to discard out of fear of future scarcity7.
Behaviorally, the senior may suddenly begin declining invitations to social gatherings that involve dining out, masking their inability to afford a restaurant meal with excuses of fatigue. They may exhibit dizziness, confusion, or increased lethargy—symptoms easily misdiagnosed as cognitive decline, but which are frequently the direct result of hypoglycemia from skipped meals or medication taken on an empty stomach7. The objective for observers is not to strip the senior of their agency through aggressive surveillance, but to recognize these quiet signals and offer support that fiercely protects their autonomy and pride.
Designing Dignity-Centered Policy and Restorative Interventions
The eradication of senior hunger requires the dismantling of systems built on suspicion and the construction of infrastructure engineered for dignity. Older adults must never be treated as passive, unfortunate recipients of charity; they are autonomous citizens deserving of respect, choice, and absolute nutritional security7.
Dignity-centered assistance begins with choice-based distribution. Traditional food pantries that hand out pre-packed boxes of arbitrary goods strip the user of their agency. Transitioning to “client-choice” models, where seniors shop the aisles of a pantry as they would a traditional grocery store, restores the basic dignity of selecting foods that meet their specific cultural, medical, and personal preferences7. Furthermore, the integration of policies like California’s AB 660, which standardizes chaotic date labels to prevent the premature disposal of perfectly safe food, and SB 1383, which mandates commercial food rescue, ensures a more robust, high-quality supply chain to these community distribution points.
Enrollment for public benefits must be radically simplified. The expansion of programs like ESAP should be universal, utilizing existing data from Medicare or Social Security to automatically enroll eligible seniors in SNAP without requiring them to navigate labyrinthine portals or submit to degrading interviews7. Delivery systems for homebound seniors must offer flexible timing, utilize familiar and consistent delivery personnel to build trust, and ensure that the packaging of the food can be easily opened by hands suffering from severe arthritis7.
Ultimately, the healthcare sector must fundamentally alter its operational paradigm to embrace “Food as Medicine.” Recognizing that malnutrition drives astronomical excess healthcare spending, the Centers for Medicare & Medicaid Services (CMS) must formally integrate medically tailored meals and grocery stipends as fully reimbursable, standard medical benefits7. The passage of the Affordable Care Act’s Section 3025 (Hospital Readmissions Reduction Program) already penalizes hospitals for avoidable readmissions; funding home-delivered meals upon discharge is the most economically and ethically sound mechanism to prevent frail seniors from cycling back into the emergency room36. When a hospital discharges an older adult, a prescription for thirty days of high-quality, home-delivered meals must be deemed just as critical to their recovery—and just as readily funded—as a prescription for pharmaceuticals.
Closing Synthesis: The Imperative for a New Social Contract
As the sun begins to set outside the modest apartment, the stillness is broken by a sharp, cheerful knock at the door. The elderly resident slowly makes their way to the entryway, unlatching the chain. A familiar volunteer from the local Meals on Wheels program stands in the hallway, holding a warm, nutritionally balanced meal7.
The exchange is brief, lasting perhaps no more than three minutes. They discuss the weather, the volunteer asks about a recently aching knee, and a genuine smile breaks across the resident’s face. The transaction provides the physical calories necessary for survival today, and the leftovers will provide the security needed for tomorrow. But far more importantly, the interaction pierces the suffocating veil of isolation. In that fleeting moment, the invisible wall comes down. The senior is seen, recognized, and reminded that they have not been forgotten by the world outside their door7.
Yet, a single meal delivered by an underfunded, stretched charity cannot be the terminus of the social contract. The relief provided by that knock at the door must be permanently fortified by a systemic guarantee of economic and nutritional security. The intersection of skyrocketing housing costs, stagnant SSI grants, and flat-funded federal nutrition programs guarantees that without radical intervention, millions of seniors will spend their final years engaged in a brutal calculus of survival.
A society’s morality is fundamentally judged by how it sustains its most vulnerable architects. The imperative is absolute: human beings who spent their lives building the economy, anchoring families, and shaping communities must never be forced to disappear into the shadows before their hunger finally becomes visible. The eradication of senior hunger requires moving beyond mere caloric distribution to construct a comprehensive architecture of dignity—ensuring that every older adult possesses not just the food to survive, but the profound respect they have earned.
Works cited
- Understanding the Experience of Food Insecurity by Elders Suggests Ways to Improve Its Measurement – ResearchGate, https://www.researchgate.net/publication/10588927_Understanding_the_Experience_of_Food_Insecurity_by_Elders_Suggests_Ways_to_Improve_Its_Measurement
- Hunger in San Diego, https://feedingsandiego.org/hunger-in-san-diego/
- Food Insecurity Among Older Adults Remained Elevated in 2024 – AARP, https://www.aarp.org/pri/topics/health/food-insecurity/food-insecurity-adults-50-and-older/
- New Feeding America Study Finds that 5.5 Million Seniors Faced Hunger in 2021, https://feedingmissouri.org/new-feeding-america-study-finds-that-5-5-million-seniors-faced-hunger-in-2021/
- Food insecurity by children | KIDS COUNT Data Center, https://datacenter.aecf.org/data/tables/9189-food-insecurity-by-children
- CPE Monthly: Food Insecurity in Older Adults – Today’s Dietitian Magazine, https://www.todaysdietitian.com/cpe-monthly-food-insecurity-in-older-adults/
- [20260802]_[The Senior Hunger Nobody Sees]_[Outline].docx
- Understanding Senior Food Insecurity: The Hidden Crisis Among Older Adults – YWCA Greater Los Angeles, https://www.ywcagla.org/blog-1/understanding-senior-food-insecurity-the-hidden-crisis-among-older-adultsnbsp
- SSI Federal Payment Amounts for 2026 – Social Security Administration, https://www.ssa.gov/oact/cola/SSI.html
- THE BASICS – CA4SSI, http://ca4ssi.org/the-basics
- Supplemental Security Income/State Supplementary Payment (SSI/SSP) – California Department of Social Services, https://cdss.ca.gov/inforesources/ssi-ssp
- The 2026-27 Budget: Supplemental Security Income/State Supplementary Payment (SSI/SSP) Program – Legislative Analyst’s Office, https://lao.ca.gov/publications/report/5148
- Supplemental Security Income (SSI)/ State Supplementary Payment (SSP) – California Association of Food Banks, https://www.cafoodbanks.org/wp-content/uploads/2025/02/SSISSP-Basics-Factsheet-1.pdf
- Exploring the Link Between Social and Economic Instability and COPD: A Cross-Sectional Analysis of the 2022 BRFSS – PMC, https://pmc.ncbi.nlm.nih.gov/articles/PMC12386543/
- (PDF) Exploring the association of social connections and food security among adults with uncontrolled type 2 diabetes: a population-based study – ResearchGate, https://www.researchgate.net/publication/384606497_Exploring_the_association_of_social_connections_and_food_security_among_adults_with_uncontrolled_type_2_diabetes_a_population-based_study
- Food Insecurity and Health Care Expenditures in the United States, 2011-2013, https://www.researchgate.net/publication/317599929_Food_Insecurity_and_Health_Care_Expenditures_in_the_United_States_2011-2013
- (PDF) Gardening for change: Community giving gardens and senior food insecurity – ResearchGate, https://www.researchgate.net/publication/354642879_Gardening_for_change_Community_giving_gardens_and_senior_food_insecurity
- Food Insecurity And Health Outcomes, https://www.healthaffairs.org/doi/abs/10.1377/hlthaff.2015.0645
- Senior SNAP Participation Visualization – The National Council on Aging (NCOA), https://www.ncoa.org/article/senior-snap-participation/
- Program Narrative and Factsheets – CalFresh Outreach – Providers & Partners, https://aging.ca.gov/Providers_and_Partners/CalFresh_Outreach/Program_Narrative_and_Fact_Sheets/
- Elderly Simplified Application Project (ESAP), https://stgenssa.sccgov.org/debs/program_handbooks/calfresh/assets/CalFresh/Household_Composition/Elderly_Simplified_Application_Project_(ESAP).htm
- HOUSE OF DELEGATES HANDBOOK ADDENDUM – REFERENCE COMMITTEE K (I-22) – American Medical Association, https://www.ama-assn.org/system/files/i22-refcomm-k-addendum.pdf
- Key Facts About CalFresh Beneficiaries – UCLA Latino Policy and Politics Institute, https://latino.ucla.edu/research/supplemental-nutrition-in-jeopardy-key-facts-about-calfresh-beneficiaries/
- USDA Refusal to Fund November CalFresh Benefits Threatens Food Security for 5.5 Million Californians – California Budget & Policy Center, https://calbudgetcenter.org/resources/usda-refusal-to-fund-november-calfresh-benefits-threatens-food-security-for-5-5-million-californians/
- Meals on Wheels America Issues Statement on Updated Administration Budget Proposals, https://www.mealsonwheelsamerica.org/news/meals-on-wheels-america-issues-statement-on-updated-administration-budget-proposals/
- Evaluating the Effect of a Home-Delivered Meals Service on the Physical and Psychological Wellbeing of a UK Population of Older Adults – A Pilot and Feasibility Study | Request PDF – ResearchGate, https://www.researchgate.net/publication/337028564_Evaluating_the_Effect_of_a_Home-Delivered_Meals_Service_on_the_Physical_and_Psychological_Wellbeing_of_a_UK_Population_of_Older_Adults_-_A_Pilot_and_Feasibility_Study
- Meals Enhancing Nutrition after Discharge (MEND): Findings from a Pilot Randomized Controlled Trial | Request PDF – ResearchGate, https://www.researchgate.net/publication/312117068_Meals_Enhancing_Nutrition_after_Discharge_MEND_Findings_from_a_Pilot_Randomized_Controlled_Trial
- The Older Americans Act – AARP Policy Book, https://policybook.aarp.org/policy-book/long-term-services-and-supports/public-sector-approaches-financing-long-term-services-and-supports/older-americans-act
- Senior Advocacy for Nutrition, Connection and Independence – Meals on Wheels America, https://www.mealsonwheelsamerica.org/our-work/advocacy/
- Catholic Charities’ Meals on Wheels continues serving local seniors despite cutbacks and challenges – Las Vegas Weekly, https://lasvegasweekly.com/news/2025/jul/10/catholic-charities-meals-on-wheels-continues/
- 2025-07-10-Las-Vegas-Weekly – Issuu, https://issuu.com/gmgproduction/docs/2025-07-10-las-vegas-weekly/11
- An Open Access Journal of The Gerontological Society of America – Oxford Academic, https://academic.oup.com/innovateage/article-pdf/4/Supplement_1/NP/39455751/igaa057.pdf
- Nutritional Vulnerability in Older Adults: A Continuum of Concerns – PMC – NIH, https://pmc.ncbi.nlm.nih.gov/articles/PMC4445877/
- Older Americans Act: Greatest economic and social needs of rural older adults – National Rural Health Association – NRHA, https://www.ruralhealth.us/getmedia/3ed469a0-255b-449f-be6d-0d53face4967/NRAFI-Policy-Paper-(OAA-FINAL,-PDF).pdf
- Medically Tailored Meals: A Case for Federal Policy Action – MDPI, https://www.mdpi.com/2227-9032/13/22/2899
- Does Participation in Home-Delivered Meals Programs Improve Outcomes for Older Adults? Results of a Systematic Review – ResearchGate, https://www.researchgate.net/publication/279181939_Does_Participation_in_Home-Delivered_Meals_Programs_Improve_Outcomes_for_Older_Adults_Results_of_a_Systematic_Review